• The Peptide Briefs Top Ten for Oct 22 to Oct 29, 2026

    The Peptide Briefs Top Ten for Oct 22 to Oct 29, 2026

    The week FDA looked the other way, and nine other things that mattered

    Originally published on Substack

    Subscribe

    1. HHS issues an enforcement discretion policy for six peptides (Oct 28)

    HHS announced it will not pursue enforcement against state licensed pharmacies that compound six peptides: BPC 157, TB 500, KPV, MOTS c, Epitalon and Semax. FDA still has to decide formally whether they belong on the 503A bulks list. This is not an approval. Government scientists reportedly warned the evidence is limited. Our grades do not change: BPC 157 stays at C.

    Sources: NCPA (ncpa.org/newsroom/qam/2026/10/29/fda-grants-enforcement-discretion-compounding-six-peptides); Ermer and Suter (ermersuter.com/2026/10/28/midweek-update-346/)

    2. The fine print, according to one law firm’s summary

    A law firm’s analysis of the policy reports these conditions: it covers 503A pharmacies, not 503B outsourcing facilities; compounding must be patient specific, with no office stock or wholesale; each product may contain only one listed peptide, so blends fall outside it; the ingredient must come from an FDA registered manufacturer that follows current good manufacturing practice and appears on the certificate of analysis; testing must cover identity, purity, potency and impurities; and state pharmacy law must allow it. The same summary says it creates no legal rights, can be revisited, and does not bind states. This is a secondary source. Check the Federal Register notice before relying on any detail.

    Source: Lumalex (lumalexlaw.com/2026/10/29/hhs-opens-a-temporary-door-for-peptides/)

    3. What happens next: a notice and a comment window

    The law firm summary says the notice is scheduled for Federal Register publication on October 30, followed by a two week comment period. It estimates that formal addition to the bulks list could take 12 to 24 months and says FDA’s advisory committee plans to review five more peptides in February 2027. Those are one source’s reading, so confirm the dates when the notice posts.

    Source: Lumalex (link above)

    4. An Australian coroner links an actor’s death to injected peptides

    On October 28, Victorian coroner David Ryan delivered findings on the death of Richard Norton, a 75 year old Australian actor, stuntman and martial arts instructor who died at Melbourne’s Alfred Hospital on March 30, 2025. The coroner found he went into cardiac arrest after injecting two unapproved peptides, CJC 1295 and ipamorelin, and that his death resulted from complications of their use. The coroner also found he had taken more than he was prescribed.

    Two details matter here. First, this was not a gray market purchase. A doctor prescribed the peptides, and a licensed compounding pharmacy in Queensland made them. Second, the case is described as believed to be the first confirmed Australian death linked to unapproved peptide use. The coroner recommended that Australia’s Therapeutic Goods Administration review the benefits and safety risks of these peptides and consider further restrictions. The TGA says it is assessing the risks. The Medical Board of Australia earlier found the prescribing doctor’s practice “is or may be unsatisfactory” and imposed a caution and conditions.

    What we do not know: what the TGA will do, the exact amounts involved, and whether other deaths exist. The coroner’s wording is that the death was triggered by the injections. News reports also mention other health history, and we are not drawing conclusions beyond the findings.

    Why it belongs in this week’s list: it arrived the same day the United States moved the opposite direction on compounding. A prescription and a licensed pharmacy are safeguards, not guarantees. The evidence for these peptides in humans remains limited, and a clinical expert in the Australian case reportedly found insufficient evidence that they are safe, effective or beneficial for human use.

    Sources: ABC News Australia (abc.net.au/news/2026-10-29/victoria-peptide-death-coroners-report-richard-norton/107320590); OzArab Media summary (ozarab.media/coroner-urges-review-of-peptide-restrictions-after-richard-nortons-death/)

    5. Lilly reports retatrutide topline results against Ozempic (Oct 28)

    In the Phase 3 TRANSCEND T2D 2 trial, 1,298 adults with type 2 diabetes were randomized to retatrutide 9 mg, retatrutide 12 mg or Ozempic 2 mg. Lilly reports weight loss of 19.5 percent and 20.9 percent for the two retatrutide doses versus 9.4 percent for Ozempic, and A1C reductions of 2.2 percent versus 1.8 percent. Discontinuation because of side effects was 4.8 percent and 7.9 percent versus 2.7 percent. Caveats: topline data from the sponsor, open label design, and retatrutide is not approved by any regulator. This is a trial of a drug under study, not a reason to trust anything sold online under the same name.

    Source: BioPharm International (biopharminternational.com/view/lilly-s-retatrutide-doubles-ozempic-s-weight-loss-in-first-phase-3-head-to-head-trial)

    6. A watchdog petitions FDA to say no

    The Partnership for Safe Medicines filed a citizen petition asking FDA not to allow compounding of the peptides the advisory committee recommended. It calls them untested and poorly defined, and says it bought five vials from telehealth services as part of its argument. The organization’s page is dated October 26, but the text says the petition was filed October 16. We list both dates because the sources differ.

    Source: Partnership for Safe Medicines (safemedicines.org/2026/10/october-26-2026-psm-cp.html)

    7. Telehealth companies line up

    Time ran a piece titled “The Peptide Rush Has Begun,” and a law firm summary of news coverage says Hims and Hers and Noom are reportedly considering or planning peptide offerings. We could not open the Time article, so treat this as reported, not confirmed. What to watch: what these companies actually launch once the notice is published.

    Sources: Time (time.com/article/2026/10/28/peptide-rush-has-begun/); Ermer and Suter (link above)

    8. A sterility recall gets its FDA classification

    Apothecary Pharma LLC recalled 22 lots of compounded tirzepatide vials on September 24, and FDA classified the recall on October 8. Coverage says no illnesses are tied to this recall and that FDA rated the chance of serious harm as remote. FDA’s March warning letter cited serious deficiencies in sterility protocols. The recall is a reminder that compounded does not mean tested for sterility by default.

    Source: Boston Globe (bostonglobe.com/2026/10/21/business/glp-1-alternative-drugs-face-nationwide-recall/)

    9. A second sterility recall in the FDA Enforcement Report

    Carolina Infusion LLC of Ridgeland, South Carolina appears in the FDA Enforcement Report for compounded semaglutide syringes, with the reason given as a lack of sterility assurance. We have not verified the event number or dates, so we are not repeating them.

    Source: FDA Enforcement Report record

    10. Adjacent: early human data for a partial reprogramming therapy

    A newsletter summary reports early Phase 1 data for Life Biosciences’ ER-100, an experimental gene therapy for optic neuropathies, with no serious safety signals and visual field improvement in 2 of 3 glaucoma participants. Three people is a safety signal, not an efficacy result. We have not read the primary release.

    Source: Fight Aging newsletter, October 26 (fightaging.org/archives/2026/10/fight-aging-newsletter-october-26th-2026)

    WHAT WE’RE WATCHING NEXT WEEK

    The Federal Register notice and comment window; whether the final policy text matches the summaries; any state pharmacy board response; and the full retatrutide data when it is presented at a medical meeting.

    ONE THING TO REMEMBER

    Access changed this week. The evidence did not. A policy can open a door. Only trials show what is behind it.

    Disclosure: I co-own Agape Compounds, a research use only peptide company. Peptide Briefs is written independently of it.

  • The FDA’s Six, Part 3: HHS Cleared the Six. Here Is What That Does and Does Not Mean

    The FDA’s Six, Part 3: HHS Cleared the Six. Here Is What That Does and Does Not Mean

    Originally publshed on Substack

    Today the Department of Health and Human Services published an interim policy in the Federal Register covering six peptides: BPC-157, TB-500, KPV, MOTS-c, Epitalon and Semax. Under it, FDA says it will not take enforcement action against licensed 503A pharmacies and physicians who compound these peptides for individual patients, provided they meet conditions on ingredient quality, manufacturing standards, labeling, safety reporting and patient-specific prescriptions. Several clinicians are reporting an effective date of Friday, October 30.

    Subscribe

    This is the end of a road that started in September 2023, when FDA moved these compounds into Category 2 of its interim bulks policy, effectively blocking pharmacies from compounding them. In April 2026 they were removed from Category 2. In July an FDA advisory committee voted narrowly, 8 to 6 on most of them, to recommend adding all six to the 503A bulks list, over the objection of the agency’s own scientific reviewers. On October 14 HHS sent this interim policy to the White House. It cleared review on October 27 and was published today.

    What it is

    Enforcement discretion. FDA is telling compounding pharmacies it will not pursue them for making these six, as long as the conditions are met. That gives clinics and telehealth providers a workable federal basis to prescribe them for the first time in three years.

    What it is not

    Approval. HHS said explicitly that the policy does not constitute FDA approval of the peptides or of any compounded product made from them. Compounded drugs are not reviewed for safety, efficacy or quality before they reach patients. HHS also said it may reconsider the policy if safety signals or product-quality problems emerge, which is a reminder that this can be withdrawn as easily as it was granted.

    It also does not bind the states. State boards of pharmacy regulate compounding on the ground, and at least one industry figure has already said some states may not follow the federal move.

    And it does not touch research-use products. A vial sold as research-use-only is outside a compounding policy entirely. Nothing in today’s announcement changes the legal status of that market in either direction.

    What the evidence says

    Here is the part that matters most to this library. FDA’s reviewers found no human safety studies for KPV, TB-500, MOTS-c or Epitalon, and found the BPC-157 trials too small and too short to establish safety or efficacy for any proposed use. An independent systematic review published this month in Acta Orthopaedica Belgica searched every major database through June for human BPC-157 data and came to a similar conclusion.

    So the grades here do not move. BPC-157 stays at C. TB-500 stays at C. The others hold where they are. A policy decision about who may dispense a compound is not evidence about whether it works, and this library grades evidence.

    What to watch

    The policy text itself, which should show exactly which conditions pharmacies must meet and whether specific indications are named. Any state board responses. The citizen petition filed last week asking FDA to block compounding of these peptides. And, further out, whether FDA ever starts the formal rulemaking that would put any of the six on the bulks list permanently. The advisory committee’s recommendation was non-binding, and as of today no proposed rule exists.

    Disclosure: I co-own a research-peptide vendor. That is disclosed on every page of this publication and does not affect how compounds are graded here.

    Sources
    Reuters, Oct 28, 2026: US health department to allow temporary sale of some unapproved peptides
    AJMC, Jul 31, 2026: FDA Panel Backs 6 Peptides for Compounding
    Holland & Knight, Oct 2026: Peptides at a Crossroads
    reginfo.gov, RIN 0910-ZD94, Interim Access Policy for Compounding Using Certain Peptides

  • A sterility recall, a regulatory signal, and two claims that outran their sources

    A sterility recall, a regulatory signal, and two claims that outran their sources

    What I could confirm this week in peptide news, and what I couldn’t.

    Originally posted on Substack

    There was a lot of noise in the peptide feed this week. Here is the short version: what I could confirm from a source, what I couldn’t, and what to watch.

    Subscribe

    1. Two compounded GLP-1 recalls over sterility

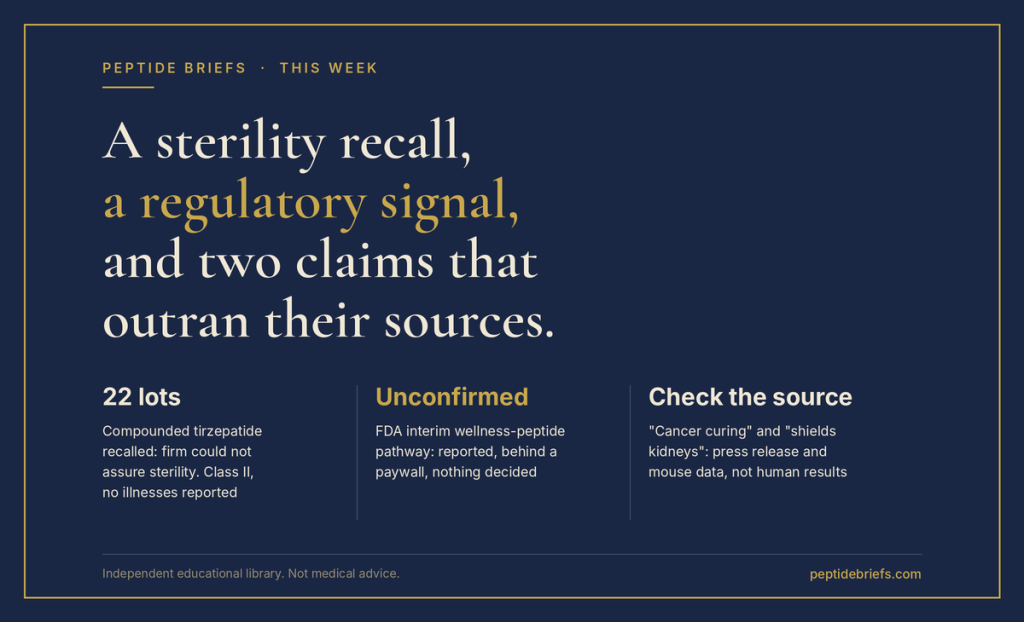
    Apothecary Pharma. Apothecary Pharma LLC, a 503B outsourcing facility in Cary, North Carolina, recalled 22 lots of compounded tirzepatide (18 mg/mL, 4 mL multi-dose vials) and one lot of an NAD+ injection. The reason given: the firm “cannot assure the product is sterile.”

    What that does and doesn’t mean:

    • It is voluntary and firm-initiated, and FDA classified it Class II.
    • No illnesses are reported in the coverage I read.
    • “Can’t assure sterility” is a documentation finding. It is not a finding that contamination was detected.
    • FDA issued a warning letter to the firm after a May 2025 inspection that cited insanitary conditions in sterile drug production. The coverage does not say whether the recall is connected to those findings, so I won’t connect them either.

    Carolina Infusion. A widely shared post also described a second recall, by Carolina Infusion, LLC of Ridgeland, South Carolina. FDA’s Enforcement Report lists it. One record I reviewed covers compounded semaglutide 3 mg/mL syringes, Class II, with the reason given as lack of assurance of sterility “related to formulation using bacteriostatic water” and “related to processing equipment used in compounded product.” That wording points at the manufacturing process, not at a contamination finding. The beyond-use dates on the lots in that record have all passed. I only reviewed one record, so I’m not stating how many products or lots the recall covers.

    Takeaway: for any injectable, the paperwork is part of the product. If a manufacturer can’t document the process, that is the story, whether or not anyone got sick.

    1. FDA may be weighing an interim path for “wellness” peptide compounding

    The Capitol Forum reported on October 21 that FDA is seeking an interim pathway that would allow compounding of certain unapproved wellness peptides before final rulemaking. The article is paywalled, so I only have the headline and a short summary. I don’t know the scope, which peptides, or any dates.

    So: a signal, not a decision. Nothing has changed in what is allowed today. If details become public, I’ll cover them properly.

    1. Enforcement is moving past the “research use only” label

    Eli Lilly filed suit in August against six U.S. companies over unauthorized retatrutide, and says it referred information on more than 200 individuals and entities to authorities. It is also asking payment processors, platforms and shippers to stop unauthorized sales. A law-firm summary of the cases notes that FDA treated one seller’s retatrutide as an unapproved new drug in March, despite research-use-only wording, relying on the company’s website and the claims it made.

    The pattern worth noticing is that intended use is judged from conduct, not from the label. Marketing, social posts, and how a seller talks to customers all count. That applies to every seller and every influencer in this space, and it is a good reason to be skeptical of anyone who says “it’s labeled RUO, so anything goes.”

    Retatrutide itself is still investigational. Per the same summary, FDA says it cannot be compounded.

    1. Two claims that outran their sources

    SenoMune-0257. A viral post called it a “cancer curing peptide” that “completed pre-clinical studies successfully.” The only coverage I found is a trade-press article built on a company press release from Immorta Bio. It describes a nine-amino-acid, AI-designed peptide intended to train immune cells to remove senescent cells, framed around diseases of aging. It does not call it a cancer treatment, it gives no data on models or results, and human evaluation is described as anticipated before year-end, not started.

    A MOTS-c kidney study. Another post said MOTS-c “could be the peptide that shields kidneys from diabetes,” citing a mouse and cell-culture paper. I could not find that paper, so I can’t confirm the details. Even if it holds up exactly as described, mice and lab cells point to where to look. They don’t show what happens in people.

    A quick filter for any viral peptide post:

    1. Mice, cells, or humans?
    2. Correlation or intervention?
    3. Is there a DOI? If the poster can’t link it, treat it as a rumor.

    What I’m watching

    • Any FDA detail on an interim wellness-peptide pathway.
    • The retatrutide court case over classification and jurisdiction.
    • A DOI for the MOTS-c kidney paper.

    This is a news summary and not medical, legal or purchasing advice.

    Sources

    • Managed Healthcare Executive, October 21, 2026: Apothecary Pharma recall of compounded tirzepatide and NAD+ vials over sterility concerns (managedhealthcareexecutive.com)
    • FDA Enforcement Report, Carolina Infusion, LLC (accessdata.fda.gov)
    • The Capitol Forum, Health Care Weekly, October 21, 2026 (thecapitolforum.com), paywalled
    • Vedder Price, “Lilly’s Retatrutide Lawsuits Spotlight Expanding Enforcement Risk for the Peptide and GLP-1 Industry” (vedder.com)
    • RuntimeWire, “Immorta Bio completes preclinical studies for AI-designed senolytic peptide” (runtimewire.com)

    Disclosure: I co-own Agape Compounds, a research-use-only peptide company. Peptide Briefs is written independently of it.

  • The Peptide Briefs Top Ten: Week of Oct 19, 2026

    The Peptide Briefs Top Ten: Week of Oct 19, 2026

    What the internet argued about this week, and what each topic really means.

    Every week, ten peptide topics take over the feeds, the news and the comment sections. This is the list, in order, with one line on why each matters.

    How it’s built: news coverage, Reddit and Substack discussion, and public posts on X, ordered by editorial judgment. It is not a measured ranking. I can’t measure X directly, and every claim below is attributed to its source.

    1. FDA’s interim access policy. Sent to the White House on Oct 14. The text isn’t public. Enforcement discretion is not approval, and the evidence grades haven’t moved.
    2. GLP-1 compounds. They account for most online peptide conversation, by a wide margin.
    3. Retatrutide. Lilly’s TRIUMPH-1 topline results are driving interest. The data aren’t yet peer-reviewed, and the drug isn’t approved.
    4. Platforms writing the rules. TikTok is reported to block searches for some peptide names. A screenshot of an Apple letter shows it objecting to reconstitution calculators. Neither is confirmed by the company.
    5. FDA versus “research use only.” August warning letters made the point that a disclaimer doesn’t outweigh the rest of a site’s marketing.
    6. COAs and “verified.” Everyone says the word. Few define it. Does it mean the lab confirmed the report, or the seller uploaded a PDF?
    7. Harm stories versus the access push. Media reports of people hurt by peptides are running alongside the political push for wider access.
    8. Influencer hype and expert warnings. Doctors in several countries are pushing back on social-media promotion.
    9. Access politics and polls. Sponsor-funded polling shows support for pharmacy access. Read it with the sponsor in mind.
    10. Mitochondrial peptides. MOTS-c, SS-31 and Humanin keep coming up, often with a level in the body mistaken for an outcome.

    WHAT MOVED THIS WEEK
    This is the first edition, so there is nothing to compare yet. Next week this section will show what moved up and down.

    YOUR TURN
    Which topic would you move to #1? Reply and tell me.

    Get the Top Ten every Thursday: subscribe on Substack

    I co-own a research-peptide vendor, and Peptide Briefs is editorially independent of it. Nothing here is medical advice.

  • The FDA’s Six, Part Two: a peptide policy is sitting at the White House. Here’s what it would and wouldn’t change.

    The FDA’s Six, Part Two: a peptide policy is sitting at the White House. Here’s what it would and wouldn’t change.

    Find Part One Here

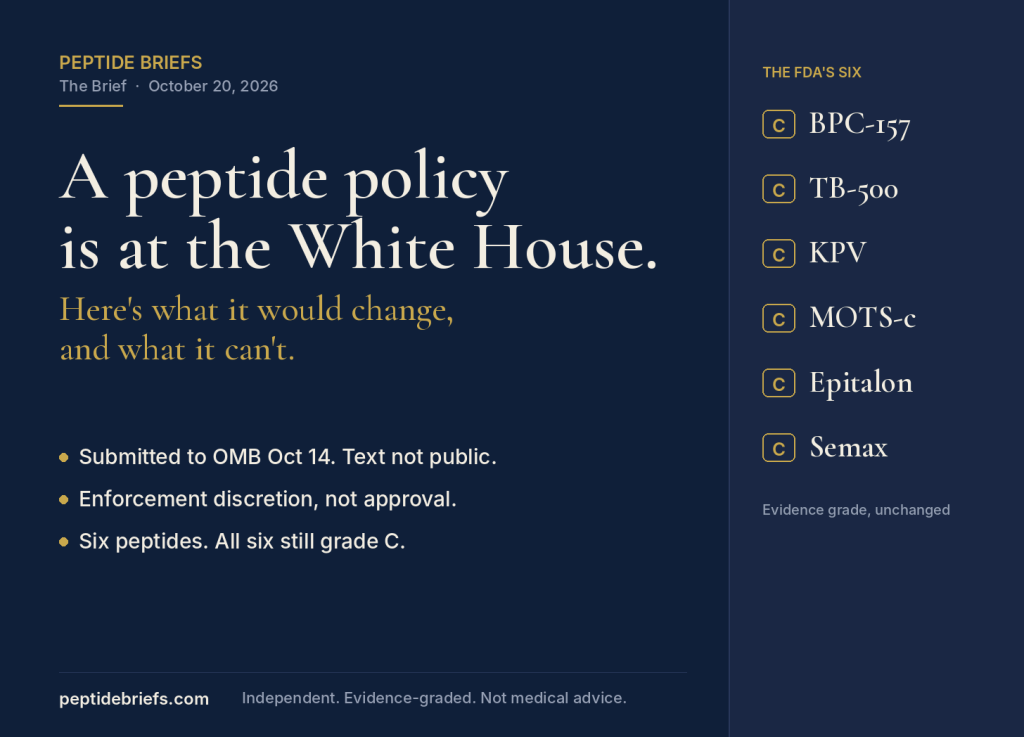
    On October 14, HHS and the FDA sent a document called “Interim Access Policy for Compounding Using Certain Peptides” to the White House Office of Management and Budget for review. It is listed as pending. Reuters reported the submission the next day, and within 48 hours several headlines had the FDA “fast-tracking” peptides.

    It isn’t. Here is what actually happened, what the document most likely says, and what it cannot do.

    Where this came from:

    In September we covered what the human evidence shows for the six peptides an FDA advisory committee voted toward the compounding list in July: BPC-157, KPV, TB-500, MOTS-c, Epitalon and Semax. Short version: all six sit at C on our scale. Cell and animal data, little or no controlled human data, and in several cases no published human trial at all.

    The votes were close and they went against the agency’s own scientists. FDA staff had recommended against all seven peptides under review on June 29, citing poorly characterized substances, limited human data and immune-reaction risk. BPC-157, KPV and TB-500 each passed 8 to 6 with one abstention. Emideltide (DSIP) failed 6 to 7. Roughly half the reconstituted committee was reported to have ties to peptide clinics or businesses.

    A committee vote does not put anything on the 503A bulks list. That takes a proposed rule, a comment period and a final rule. The last time FDA did this for a batch of ten substances, the proposed rule came in 2016 and the final rule in 2019.

    What the October 14 document most likely is

    Nobody outside government has read it. But the title says “interim” and “access,” and the FDA already runs an interim policy for nominated bulk substances. Under that policy, a substance in Category 1 can be compounded by a state-licensed 503A pharmacy while the agency keeps evaluating it, because the FDA says it does not intend to enforce against that use. Category 2 substances, where BPC-157 and friends sat from 2023 until April of this year, get no such discretion.

    So the most likely shape is this: the six move into Category 1, with conditions. A prescriber writes a prescription for one patient. A licensed pharmacy compounds it from bulk material that meets whatever sourcing and testing standards the policy names. The FDA agrees not to pursue that pharmacy for it, for now.

    What it would not do

    1. It would not approve anything. Enforcement discretion is the agency saying what it will not prosecute. The peptides would remain unapproved drugs with the same evidence base they have today.
    2. It would not be permanent. A guidance document can be narrowed or withdrawn without a comment period. The compounded semaglutide and tirzepatide discretion periods ended the same way.
    3. It would not cover products sold as research chemicals, dietary supplements or through 503B outsourcing facilities. The channel it opens is prescription-only, through a pharmacy.
    4. It would not bind state pharmacy or medical boards, which can still say no.
    5. It could be limited by route. Some committee members tied their yes votes to specific routes of administration, and the policy could follow them.

    That third point deserves a second look, because it is the one the headlines skip.

    The other half of the story

    While the access story got the attention, enforcement went the other way. On August 24 the FDA sent five warning letters to online peptide vendors. The agency’s reasoning is worth knowing exactly: a “research use only” label did not outweigh evidence the products were intended for people, and the evidence it pointed to was bacteriostatic water sold for mixing and dosing calculators offered alongside the vials.

    On September 18 a warning letter went to a compounder whose GLP-1 products with added B12 or niacinamide were, in the FDA’s view, essentially copies of approved drugs. The same letter questioned prescriptions generated from preselected menu options on telehealth platforms. And in August the developer of retatrutide filed six lawsuits against sellers and reported more than 200 referrals to regulators.

    Read those two threads together. The administration is building a narrow, licensed, prescription path for six C-grade peptides, and at the same time the agency is telling the gray market that the label on the vial is not a defense if the rest of the website says otherwise.

    What happens next

    Date

    What

    Now

    OMB review of the interim policy; no deadline, no public text

    Before end of Feb 2027

    Second advisory committee meeting on GHK-Cu, LL-37, Dihexa, Melanotan II and PEG-MGF; date not set

    2027

    A proposed rule for the bulks list, if FDA accepts the July votes

    Late 2027 to 2028

    A final rule, on the 2016-to-2019 precedent

    Jan 2029

    Whatever survives the 2028 election

    If the policy comes out, the things to read first are the conditions: which lab standards the bulk material has to meet, whether the FDA-registered facility and certificate-of-analysis language applies, and whether any route is excluded. Those conditions will say more about where this is going than the headline.

    What it means for the grades

    Nothing. A grade here is a statement about evidence, and no evidence changed this month. Access and evidence are different questions, and a policy that opens the first does not answer the second. If a controlled human trial of any of the six publishes, you will read about it here, and the grade will move then.

    The six pages, for reference: BPC-157, TB-500, KPV, MOTS-c, Epitalon, Semax.

    Disclosure: I co-own a research-peptide vendor. That is stated on every page here, and this library does not link to it.

    Peptide Briefs is an independent reference. Nothing here is medical advice or a recommendation to use any compound.

    Also published on Substack

  • The Retatrutide Court Case: What’s Actually at Stake

    Troy Snyder, Sept 2026

    If you’ve been tracking Retatrutide’s evidence record with us — the TRIUMPH trials, the June Lancet publication, the EASD data landing September 30 — there’s a separate story developing this week that has nothing to do with clinical data and everything to do with whether any of it matters in the way you’d expect.

    On September 21, the DOJ filed a letter in Eli Lilly v. FDA (7th Circuit, No. 26-1301), a case that’s been quietly working through the courts and is about to get a lot louder. Oral arguments are Thursday, September 24, 9:30am, Chicago.

    What the case is actually about

    Strip away the legal language and it comes down to one question: is Retatrutide a peptide drug, or is it a protein/biologic?

    That sounds like a technicality. It isn’t. The two classifications sit inside completely different regulatory frameworks, and which one Reta lands in determines the entire competitive landscape around it going forward.

    • Lilly’s position: Retatrutide should be classified as a protein/biologic.
    • FDA’s position: It’s a peptide drug and doesn’t meet the agency’s own definition of a protein.

    The DOJ’s letter this week is procedural but consequential — it’s pointing the appeals court toward a recent Seventh Circuit precedent (Franco v. Chobani, 2026) holding that when an agency’s interpretation of its own scientific definitions is at issue, that interpretation can still carry significant weight with courts, even post-Chevron. In plain terms: DOJ is telling the judges not to second-guess FDA’s classification lightly.

    Why the classification actually matters

    If Reta gets classified as a biologic:

    • Follow-on/generic-equivalent products go through the biosimilar pathway instead of the standard generic route — a slower, more expensive approval process historically reserved for large, complex molecules.
    • 503A/503B compounding pharmacies lose their normal drug-compounding exemptions for biologics, which changes who can legally produce Reta-adjacent formulations and under what rules.

    If Reta stays classified as a peptide drug:

    • It remains inside the traditional drug framework, where standard generic pathways apply.
    • 503A/503B compounding exemptions can still apply, provided other regulatory requirements are met.

    Neither outcome is good or bad in the abstract but they’re genuinely different worlds for anyone tracking availability, pricing, and the broader compounding/RUO ecosystem that sits adjacent to this compound’s supply chain.

    What this means for the grey market

    The 503A/503B compounding question isn’t just a pharmacy-industry detail, it’s the actual bridge between this court case and the broader research-peptide ecosystem, RUO sourcing included.

    If Reta moves into the biosimilar framework, compounding pharmacies lose the exemptions that currently let them produce Reta-adjacent formulations more freely. That tends to push demand in one of two directions, and it’s genuinely unclear which wins out:

    • Tighter compounding rules could push more demand toward RUO/research-only channels as the compounding pathway narrows, the same pattern seen with other GLP-1 compounds when compounding pharmacies faced restrictions.
    • Or it could do the opposite: a high-profile classification fight tends to put the entire peptide category under a brighter regulatory spotlight, RUO sourcing included, not just the specific compound in litigation. Increased scrutiny on one part of the ecosystem has historically spilled over into stricter enforcement, platform bans, and payment-processor caution across the board — something we’ve experienced directly this month.

    We’re not going to speculate on which direction wins, because neither outcome is something we’d base a customer-facing claim on before it actually happens. What we can say plainly: this case is worth watching regardless of whether you buy compounded, RUO, or anything else in this space. The ruling reshapes incentives for the whole supply chain, not just Lilly’s own product line.

    What we’re watching for

    We’ll be straight about where we sit on this: we don’t have a legal opinion on how the classification question should be decided, that’s genuinely a matter for the courts to work out, and we’re not lawyers. But we do have a rooting interest, and we’re not going to pretend otherwise. If Reta stays classified as a peptide drug, the compounding and RUO ecosystem this whole site operates in keeps more room to breathe. If Lilly wins, that room narrows. That’s not a legal argument for either side, it’s just an honest disclosure of where our interest lies, same as we disclose our ownership stake in Agape on multiple pages of this site.

    Oral arguments are Thursday. A ruling likely won’t land immediately; appellate decisions in cases like this often take weeks to months after arguments, but the reasoning that comes out of Thursday’s session will be the first real signal of which way this is heading.

    We’ll cover the outcome in Grade Changes once there’s something concrete to report. For now, this is a “know it’s coming” post, not a “here’s the answer” post — and we’d rather tell you that plainly than manufacture certainty we don’t have.

    — Troy

    Peptide Briefs is an independent research library. This piece covers regulatory proceedings, not clinical evidence — Retatrutide’s evidence grade (B) is unaffected by this case and is tracked separately.