Blog

  • The Peptide Briefs Top Ten: Week of Oct 19, 2026

    The Peptide Briefs Top Ten: Week of Oct 19, 2026

    What the internet argued about this week, and what each topic really means.

    Every week, ten peptide topics take over the feeds, the news and the comment sections. This is the list, in order, with one line on why each matters.

    How it’s built: news coverage, Reddit and Substack discussion, and public posts on X, ordered by editorial judgment. It is not a measured ranking. I can’t measure X directly, and every claim below is attributed to its source.

    1. FDA’s interim access policy. Sent to the White House on Oct 14. The text isn’t public. Enforcement discretion is not approval, and the evidence grades haven’t moved.
    2. GLP-1 compounds. They account for most online peptide conversation, by a wide margin.
    3. Retatrutide. Lilly’s TRIUMPH-1 topline results are driving interest. The data aren’t yet peer-reviewed, and the drug isn’t approved.
    4. Platforms writing the rules. TikTok is reported to block searches for some peptide names. A screenshot of an Apple letter shows it objecting to reconstitution calculators. Neither is confirmed by the company.
    5. FDA versus “research use only.” August warning letters made the point that a disclaimer doesn’t outweigh the rest of a site’s marketing.
    6. COAs and “verified.” Everyone says the word. Few define it. Does it mean the lab confirmed the report, or the seller uploaded a PDF?
    7. Harm stories versus the access push. Media reports of people hurt by peptides are running alongside the political push for wider access.
    8. Influencer hype and expert warnings. Doctors in several countries are pushing back on social-media promotion.
    9. Access politics and polls. Sponsor-funded polling shows support for pharmacy access. Read it with the sponsor in mind.
    10. Mitochondrial peptides. MOTS-c, SS-31 and Humanin keep coming up, often with a level in the body mistaken for an outcome.

    WHAT MOVED THIS WEEK
    This is the first edition, so there is nothing to compare yet. Next week this section will show what moved up and down.

    YOUR TURN
    Which topic would you move to #1? Reply and tell me.

    Get the Top Ten every Thursday: subscribe on Substack

    I co-own a research-peptide vendor, and Peptide Briefs is editorially independent of it. Nothing here is medical advice.

  • The FDA’s Six, Part Two: a peptide policy is sitting at the White House. Here’s what it would and wouldn’t change.

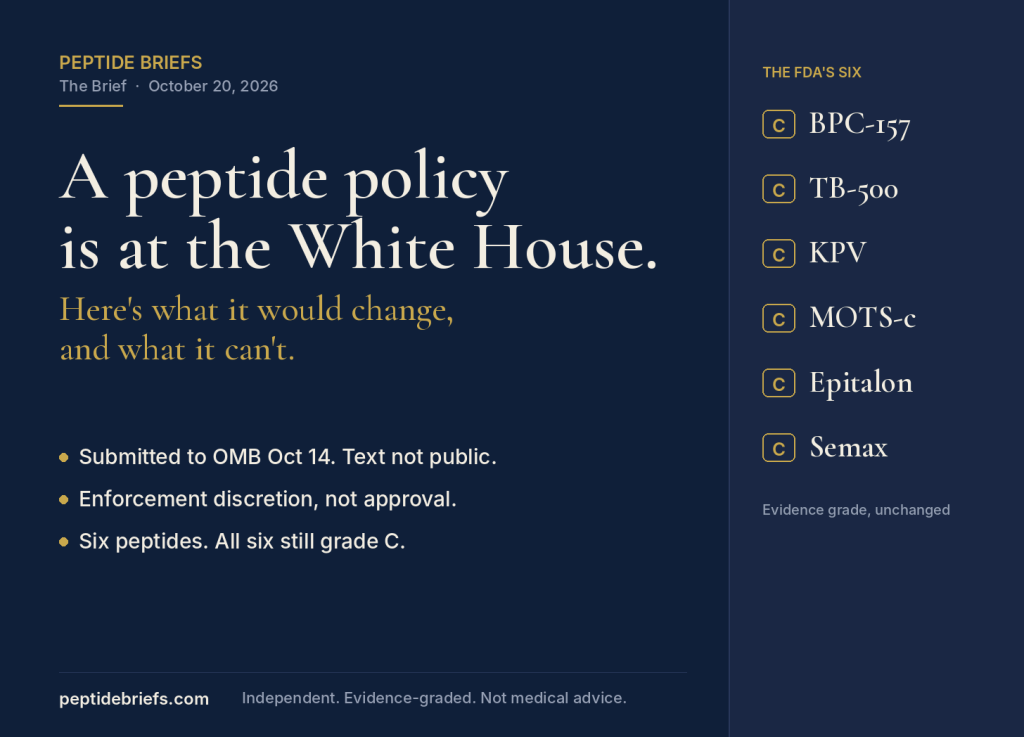
    The FDA’s Six, Part Two: a peptide policy is sitting at the White House. Here’s what it would and wouldn’t change.

    Find Part One Here

    On October 14, HHS and the FDA sent a document called “Interim Access Policy for Compounding Using Certain Peptides” to the White House Office of Management and Budget for review. It is listed as pending. Reuters reported the submission the next day, and within 48 hours several headlines had the FDA “fast-tracking” peptides.

    It isn’t. Here is what actually happened, what the document most likely says, and what it cannot do.

    Where this came from:

    In September we covered what the human evidence shows for the six peptides an FDA advisory committee voted toward the compounding list in July: BPC-157, KPV, TB-500, MOTS-c, Epitalon and Semax. Short version: all six sit at C on our scale. Cell and animal data, little or no controlled human data, and in several cases no published human trial at all.

    The votes were close and they went against the agency’s own scientists. FDA staff had recommended against all seven peptides under review on June 29, citing poorly characterized substances, limited human data and immune-reaction risk. BPC-157, KPV and TB-500 each passed 8 to 6 with one abstention. Emideltide (DSIP) failed 6 to 7. Roughly half the reconstituted committee was reported to have ties to peptide clinics or businesses.

    A committee vote does not put anything on the 503A bulks list. That takes a proposed rule, a comment period and a final rule. The last time FDA did this for a batch of ten substances, the proposed rule came in 2016 and the final rule in 2019.

    What the October 14 document most likely is

    Nobody outside government has read it. But the title says “interim” and “access,” and the FDA already runs an interim policy for nominated bulk substances. Under that policy, a substance in Category 1 can be compounded by a state-licensed 503A pharmacy while the agency keeps evaluating it, because the FDA says it does not intend to enforce against that use. Category 2 substances, where BPC-157 and friends sat from 2023 until April of this year, get no such discretion.

    So the most likely shape is this: the six move into Category 1, with conditions. A prescriber writes a prescription for one patient. A licensed pharmacy compounds it from bulk material that meets whatever sourcing and testing standards the policy names. The FDA agrees not to pursue that pharmacy for it, for now.

    What it would not do

    1. It would not approve anything. Enforcement discretion is the agency saying what it will not prosecute. The peptides would remain unapproved drugs with the same evidence base they have today.
    2. It would not be permanent. A guidance document can be narrowed or withdrawn without a comment period. The compounded semaglutide and tirzepatide discretion periods ended the same way.
    3. It would not cover products sold as research chemicals, dietary supplements or through 503B outsourcing facilities. The channel it opens is prescription-only, through a pharmacy.
    4. It would not bind state pharmacy or medical boards, which can still say no.
    5. It could be limited by route. Some committee members tied their yes votes to specific routes of administration, and the policy could follow them.

    That third point deserves a second look, because it is the one the headlines skip.

    The other half of the story

    While the access story got the attention, enforcement went the other way. On August 24 the FDA sent five warning letters to online peptide vendors. The agency’s reasoning is worth knowing exactly: a “research use only” label did not outweigh evidence the products were intended for people, and the evidence it pointed to was bacteriostatic water sold for mixing and dosing calculators offered alongside the vials.

    On September 18 a warning letter went to a compounder whose GLP-1 products with added B12 or niacinamide were, in the FDA’s view, essentially copies of approved drugs. The same letter questioned prescriptions generated from preselected menu options on telehealth platforms. And in August the developer of retatrutide filed six lawsuits against sellers and reported more than 200 referrals to regulators.

    Read those two threads together. The administration is building a narrow, licensed, prescription path for six C-grade peptides, and at the same time the agency is telling the gray market that the label on the vial is not a defense if the rest of the website says otherwise.

    What happens next

    Date

    What

    Now

    OMB review of the interim policy; no deadline, no public text

    Before end of Feb 2027

    Second advisory committee meeting on GHK-Cu, LL-37, Dihexa, Melanotan II and PEG-MGF; date not set

    2027

    A proposed rule for the bulks list, if FDA accepts the July votes

    Late 2027 to 2028

    A final rule, on the 2016-to-2019 precedent

    Jan 2029

    Whatever survives the 2028 election

    If the policy comes out, the things to read first are the conditions: which lab standards the bulk material has to meet, whether the FDA-registered facility and certificate-of-analysis language applies, and whether any route is excluded. Those conditions will say more about where this is going than the headline.

    What it means for the grades

    Nothing. A grade here is a statement about evidence, and no evidence changed this month. Access and evidence are different questions, and a policy that opens the first does not answer the second. If a controlled human trial of any of the six publishes, you will read about it here, and the grade will move then.

    The six pages, for reference: BPC-157, TB-500, KPV, MOTS-c, Epitalon, Semax.

    Disclosure: I co-own a research-peptide vendor. That is stated on every page here, and this library does not link to it.

    Peptide Briefs is an independent reference. Nothing here is medical advice or a recommendation to use any compound.

    Also published on Substack

  • WHAT ACTUALLY HAPPENS TO A PEPTIDE BEFORE IT REACHES THE VIAL

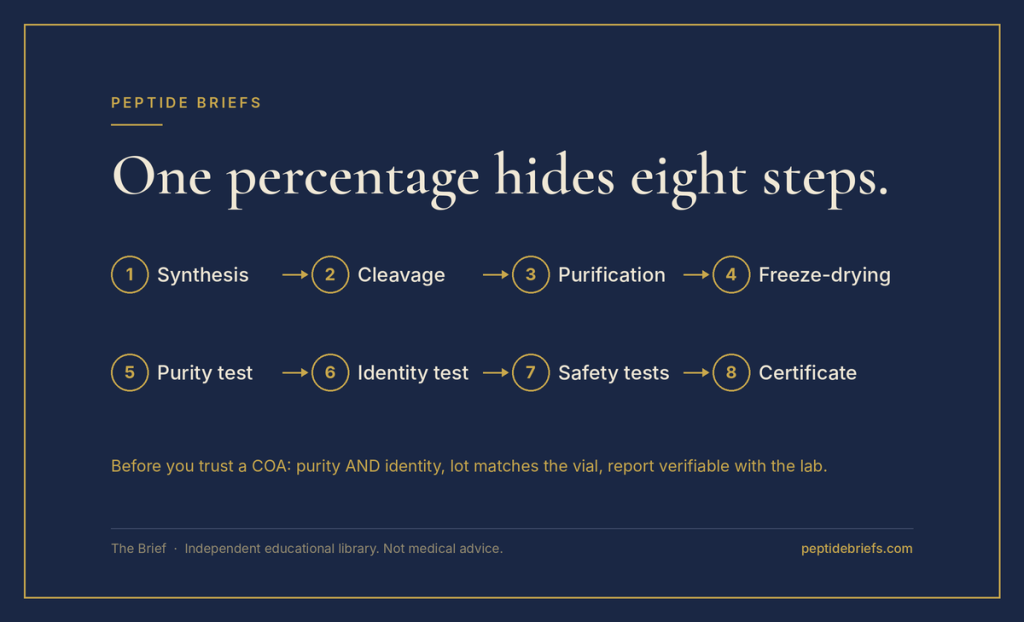
    WHAT ACTUALLY HAPPENS TO A PEPTIDE BEFORE IT REACHES THE VIAL

    Eight steps, and where each one can go wrong.

    A label says “99% pure.” It doesn’t say what happened before that number. Here is the path of one lot from chemistry to certificate, with the question to ask at each step.

    This is about manufacturing and testing. It is research-use-only information, not guidance for use in people.

    A note on where this comes from. I spent two years living in China, where I observed the peptide industry up close: I met vendors and manufacturers and visited their labs. I’m not a chemist, and this post doesn’t pretend to be a lab manual. It’s what I learned about how a lot moves from synthesis to certificate, and about which questions separate a real certificate from a PDF.

    SYNTHESIS
    Amino acids are joined one at a time on a resin bead. No step is perfect.
    Make Simple: at 99% efficiency per step, a 30-amino-acid peptide comes out roughly three-quarters full-length. The rest is near-miss sequences.
    Ask: how was the batch made, and how was the crude product cleaned up?

    CLEAVAGE
    The chain is chemically cut from the resin. What comes off is a mixture: the target, truncated pieces, deleted sequences, leftover reagents.

    PURIFICATION
    Preparative HPLC separates the target from the junk. Which fractions get kept is a judgment call, and it sets the final purity.

    FREEZE-DRYING
    The purified peptide is freeze-dried into powder. That powder is not 100% peptide. It also holds water and counterions such as TFA or acetate.
    Make Simple: “net peptide content” tells you how much of the powder is actually peptide.
    Ask: is net peptide content reported?

    PURITY TEST
    Analytical HPLC reports the share of the signal that belongs to the main peak.
    Make Simple: purity tells you how clean. It does not tell you what it is.

    IDENTITY TEST
    Mass spectrometry checks the molecular weight. Without it, a clean peak could still be the wrong molecule.
    Ask: is identity confirmed, and by what method?

    SAFETY TESTS
    Endotoxin and microbial testing are separate from purity. A certificate that lists only HPLC doesn’t cover them.

    THE CERTIFICATE
    A COA is a claim about one lot.
    Check: the lot number matches the vial. The report number can be verified with the lab itself, not just a PDF. The methods are listed. An independent lab ran it. The lab’s accreditation status is stated honestly.THE JOURNEY IN ONE LINE
    Synthesis → cleavage → purification → freeze-drying → purity → identity → safety → certificate

    THE BIG TAKEAWAY
    A single percentage hides seven other steps. Before you trust a COA, ask:

    1. Does it show purity AND identity?
    2. Is net peptide content reported?
    3. Were endotoxin and microbial tests run?
    4. Does the lot match the vial?
    5. Can the report number be verified with the lab?

    Which of these do you see missing most often?

    This post describes general peptide manufacturing and analytical practice. It makes no claim about any specific product or supplier.

    Also published on Substack.

  • Retatrutide: what the trials tested, and why a court is counting amino acids

    A viral cost estimate, a federal appeal, and what is still unknown

    Evidence grade: B (unchanged). Reviewed October 2026.

    Retatrutide was hard to miss this week. One widely shared post worked out what it would cost to give it to every American with obesity. Another reported that Eli Lilly is in court with the FDA over how many amino acids it contains. Both are worth a closer look, because each rests on a number that is easy to get wrong.

    The viral math

    The cost estimate assumed two things: a price of $1 per milligram, and 3 mg a week as a dose that works for most people.

    The dose. No trial has tested 3 mg as a maintenance dose. The Phase 2 obesity trial tested 1, 4, 8 and 12 mg. The pivotal Phase 3 trial, TRIUMPH-1, tested 4, 9 and 12 mg, with 2 mg used only as a starting step. At 80 weeks, average weight loss was 19.0% on 4 mg, 25.9% on 9 mg and 28.3% on 12 mg. What 3 mg does over a year or more is not something the published evidence can tell you.

    The price. Retatrutide is not approved in any country, so it has no list price. Lilly says it is legally available only to people in its clinical trials. A figure of $1 per milligram describes grey-market material that no regulator has examined. In August, Lilly announced six lawsuits against sellers of “research-use” retatrutide and said it had referred more than 200 others to authorities. A price for an unverified vial tells you nothing about what the medicine will cost.

    The larger argument, that treating obesity could pay for itself, may or may not be right. It needs real doses and real prices before anyone can check it.

    The court case

    Under FDA rules, a “protein” is an amino acid chain with a defined sequence that is greater than 40 amino acids long. Proteins are regulated as biologics. Shorter peptides are regulated as drugs.

    Retatrutide sits on that line. Its backbone has 39 amino acids. Attached to it is a side chain that Lilly says contains two more, which makes 41. The FDA says only alpha amino acids count and that one of the side chain’s two is not an alpha amino acid. By the FDA’s count the total is 40, which is not greater than 40.

    The classification matters for two reasons:

    • Exclusivity. Biologics get 12 years of protection from competition. New drugs get 5.
    • Compounding. Compounding pharmacies cannot make biologics. A biologic label would close the door that let pharmacies make copies of semaglutide and tirzepatide during shortages.

    Where it stands

    DateWhat happened
    March 18, 2024FDA designates retatrutide a drug, not a biologic
    September 3, 2024Lilly sues in federal court in Indiana
    September 30, 2025The court sides with FDA on the meaning of “protein,” and sends a second question, whether retatrutide is “analogous” to one, back to the agency
    February 2026Lilly appeals to the Seventh Circuit
    September 24, 2026The appeal is argued

    We found no report of a decision as of October 12.

    Whichever way the court rules, it is a decision about legal category. It adds nothing to what is known about whether retatrutide works or is safe.

    What is still unknown

    • The pivotal trial is not yet in a journal. TRIUMPH-1 was presented in full in June. As of this review we have not found a peer-reviewed publication.
    • No regulator has reviewed the safety data. Lilly has said it plans to file in early 2027. Two signals to watch are abnormal skin sensations, reported by 12.5% on the highest dose against 0.9% on placebo, and a rise in heart rate.
    • There is no head-to-head result against tirzepatide. That trial is still running.
    • TRIUMPH-2 was scheduled for full presentation at a European diabetes meeting on September 30. We have not yet reviewed it and will update the retatrutide page wScreenshot 2026-10-12 at 4.35.57 PM.pnghen we have.

    Why the grade has not changed

    Nothing this week was new evidence. The trials are the same ones we graded in September. An A needs a published pivotal trial and a regulator’s review, and retatrutide has neither yet.

    Jastreboff AM, et al. Triple-hormone-receptor agonist retatrutide for obesity: a phase 2 trial. N Engl J Med. 2023. Dose arms as summarized by Patient Care.

    AJMC: Retatrutide achieves up to 30.3% average weight loss in Phase 3 TRIUMPH-1 trial. Doses, results by arm, discontinuation rates.

    Reason: Can a new weight loss treatment escape the legal and regulatory thicket? September 10, 2026. The 40-amino-acid rule, each side’s count, exclusivity, Lilly’s six lawsuits.

    ProfPeptide: Lilly v. Kennedy, whether retatrutide is a drug or a biologic goes to the Seventh Circuit. Case timeline and dates.

    MDLinx: Inside retatrutide’s black market, Eli Lilly’s 6 new lawsuits, and a brewing FDA battle. August 18, 2026.

    Fidj Law: Drug or biologic? An Eli Lilly lawsuit could impact weight loss drug compounders.

    Lilly: new data at EASD 2026, including TRIUMPH-2 on September 30.

    The dysesthesia figures and the trial list come from the September retatrutide page on Peptide Briefs.

    Peptide Briefs is an independent reference on peptides as they appear in the scientific literature. Nothing here is medical advice or a recommendation to use any compound.

  • Three of five: what the retatrutide papers say that the press releases didn’t

    TRIUMPH-1 in NEJM, TRIUMPH-2 in The Lancet, same day. The grade stays B. Here’s what moved.

    On September 29, Lilly published two of its retatrutide Phase 3 trials in full on the same day: TRIUMPH-1 in the New England Journal of Medicine and TRIUMPH-2 in The Lancet. With TRANSCEND-T2D-1, published in The Lancet in June, that makes three of the five reported Phase 3 results peer-reviewed. Two remain company topline releases.

    The grade on Peptide Briefs stays B. This post is about why, and about what the papers say that the May and July press releases didn’t.

    Two numbers, both correct

    Lilly’s May headline for TRIUMPH-1 was 28.3% weight loss at 12 mg. The NEJM paper’s primary result is 25.0%. Both appear in Figure 1 of the paper, and the difference is not a correction; it’s two questions. The efficacy estimand asks what happens if every participant stays on drug for 80 weeks. The treatment-regimen estimand, which NEJM reports as primary, counts the people who stopped. Across all three doses the peer-reviewed numbers are 17.6%, 23.7% and 25.0% vs 3.9% on placebo, against topline figures of 19.0%, 25.9% and 28.3%.

    When a vendor or a headline quotes the higher figure, it isn’t wrong. It’s the optimistic one. The same applies to TRIUMPH-2’s 20.8%; the Lancet intention-to-treat number is [insert from paper].

    What TRIUMPH-2 adds

    TRIUMPH-2 is the type 2 diabetes cohort: 1,152 adults, 80 weeks, 4, 9 or 12 mg vs placebo. People with type 2 diabetes reliably lose less on incretin drugs than people without it, and 20.8% at 12 mg is the largest weight loss reported in that population. A1C fell 1.4 to 1.6 points from a 7.7% baseline vs 0.2 on placebo, and up to 40% of participants reached an A1C below 5.7%, the non-diabetic range. Triglycerides fell 39.5%, systolic blood pressure 10.8 mmHg, and hsCRP 58.3% at the top dose.

    What the safety tables add

    Three things the press releases didn’t lead with.

    Dysesthesia. A skin burning or tingling sensation occurred in 12.3% of participants on 9 mg and 12.5% on 12 mg in TRIUMPH-1, against 0.9% on placebo. It isn’t a known GLP-1 or GIP effect; the working assumption is the glucagon component. Lilly reports most cases were mild and resolved on treatment.

    Dropouts by dose don’t line up across trials. In TRIUMPH-1, discontinuation for adverse events rose with dose: 4.1%, 6.5%, 11.2% vs 4.6% placebo. In TRIUMPH-2 the middle dose had the most: 3.8%, 11.6%, 7.7% vs 4.9%. Two trials, two patterns; the honest reading is that we don’t yet know the dose-tolerability curve.

    Orthostatic hypotension. 8.8% at 12 mg vs 0.9% placebo in TRIUMPH-1. Small in absolute terms, ten-fold relative.

    Heart rate, the question most readers have asked, isn’t in the main NEJM tables. It’s in the supplementary appendix, and the page will be updated when we’ve read it rather than summarized from a summary.

    Why B, not A

    A on our scale means the full Phase 3 program is peer-reviewed and a regulator has reviewed the safety file. Three of five is not the program. Lilly says the BLA goes to FDA in Q1 2027; nothing has been reviewed yet. TRIUMPH-5, the head-to-head against tirzepatide, and the 10,000-participant outcomes trial are still running.

    B is not a hedge. It’s the largest weight-loss effect ever recorded in a drug trial, replicated three times in peer-reviewed form, with a safety profile that’s heavier than tirzepatide’s at the top doses and one new adverse event that needs explaining. That’s what B means.

  • What a $150,000 Group Buy Teaches About Reading a COA

    What a $150,000 Group Buy Teaches About Reading a COA

    In July, a grey-market peptide “group buy” collapsed and its members were out roughly $150,000. TitrateLab traced the money on-chain and published the details; Rick Gold at OHM Peptides separately described the same trick a month later. I’d point you to both pieces rather than retell them. What interests me is the part that had nothing to do with blockchains.

    The certificates of analysis never held up.

    Some resolved, on the testing lab’s own website, to entirely different companies. Others failed lookup altogether. The vendor’s name had been pasted onto reports that belonged to someone else. Every buyer who lost money had a PDF that looked right, and the PDF was real. Only the name at the top was fake.

    This is worth sitting with, because it inverts the usual advice. “Check the COA” is not enough. A fraudulent seller who is any good at this will hand you a genuine COA. The question is whether the COA is theirs.

    Three checks that would have caught it

    Look up the report ID on the lab’s site, not the vendor’s. Janoshik, and most serious labs, let you enter a report number and see the original. If the vendor name on the lab’s copy doesn’t match the vendor selling to you, stop.

    Match the lot number on the vial to the report. A COA for lot 2407-A tells you nothing about the vial marked 2409-C in your hand. Vendors reuse a good report across batches more often than anyone admits.

    Call the lab. This sounds excessive until you’ve done it once. A real third-party lab will confirm that a report number exists and who commissioned it. A vendor who discourages you from calling has told you what you need to know.

    What “verified by customers” means

    When the promoter in the TitrateLab piece was asked about testing, the answer was that it had been done “by customers.” That phrase should be a full stop. Customer testing is unverifiable by definition: you’re taking a stranger’s word for a stranger’s lab work. It’s the COA equivalent of “trust me.”

    The uncomfortable part

    I co-own a research-peptide vendor, disclosed on every page of this site. Earlier this year I sourced retatrutide through a contact I’d met and vetted in person, with a clean-looking COA. Two lots failed identity testing at an independent lab. The certificate had looked fine. I hadn’t asked the right questions either.

    That’s why the checklist exists. It’s one page, eight questions, and it’s the sequence I now run on every batch before it’s listed anywhere. It won’t stop a determined fraud. It will stop the lazy ones, which is most of them.

    [Download the Counterfeit Peptide Red Flag Checklist]

    Sources: TitrateLab, “The $150,000 rugpull we warned everybody about,” July 2026. Rick Gold / OHM Peptides, X, August 27, 2026. Research use only; nothing here is advice on use.

  • The FDA’s Six: What the Human Evidence Actually Shows

    On July 23-24, 2026, something unusual happened at the FDA’s White Oak campus. The Pharmacy Compounding Advisory Committee, a panel that exists to give the agency outside expert advice, voted against FDA staff’s own written recommendations six times in a row. Reporters in the room described an audible gasp when the first tally was read.

    The result: BPC-157, TB-500, Semax, KPV, MOTS-c, and Epitalon all received committee recommendations for inclusion on the FDA’s 503A Bulks List, the mechanism that lets licensed compounding pharmacies legally prepare patient-specific prescriptions. A seventh compound, Emideltide (DSIP), was voted down.

    This is not FDA approval. It’s not even a final decision. It’s a non-binding recommendation, and as of this writing, two months later, the FDA hasn’t acted on it. Formal rulemaking, if it happens, typically takes 8-12 months.

    But the vote raises a question worth answering properly: what does the actual human evidence say about these six compounds? Not the mechanism papers, not the mouse studies people cite as if they settle the matter. The human data specifically. Here’s the honest picture, compound by compound.

    BPC-157

    Grade: D. Plausible mechanism, essentially no human evidence.

    BPC-157 has zero completed human randomized controlled trials. That’s the single fact that matters most here, and it’s worth sitting with before anything else.

    The closest thing to human-scale data is a recent retrospective count of 1,039 documented users, tracked from nadir to follow-up. That’s a real number, but it measures something different than most people assume: it tells you how many people used the compound, not whether it worked. A usage count and an efficacy result are two different questions, and conflating them is the most common error in how this compound gets discussed.

    The clinical history is also more instructive than most coverage lets on. The original research trail goes back to PLIVA, the Croatian pharmaceutical company that worked with discoverer Predrag Sikiric. PLIVA registered early-stage trials around 2000 that were never published. The research was sold to GSX in 2006, and GSX abandoned it. A separate trial in Tijuana in 2015 was also canceled with no data released. Multiple companies with real resources picked this compound up and walked away. That’s a different story than “suppressed because it works,” but it’s also not nothing.

    TB-500

    Grade: D. Same evidence category as BPC-157.

    TB-500 (a synthetic fragment of Thymosin Beta-4) has an extensive preclinical literature on tissue repair, cell migration, and wound healing. None of it has translated into a completed human clinical trial for the injectable research compound as it’s commonly sold.

    The mechanistic story is genuinely interesting; it’s thought to coordinate the movement of cells involved in tissue repair, which is why it shows up so often in sports medicine and regenerative medicine discussions. But “mechanistically interesting” and “shown to work in humans” remain two separate claims, and only the first one currently has support.

    Semax

    Grade: D, with an asterisk worth understanding.

    Semax has a real research history, just not one that shows up cleanly in a PubMed search. A meaningful share of the literature on Semax (and several other Russian-developed compounds, including some of the older bromantane and actovegin research) exists in Russian-language journals that were never translated or indexed in the databases most Western researchers default to.

    This matters because “no human trials” and “no human trials I can find in English” are different claims, and the discourse around Semax tends to treat them as identical. To be direct about the limits of this caveat: this is a well-documented pattern in the space, and it’s a real gap in how evidence gets surfaced, but it isn’t a claim we’ve personally verified paper-by-paper. Treat it as an important qualifier, not a settled fact that resolves the evidence question in Semax’s favor.

    KPV

    Grade: D. The strongest mechanism of the six, and still zero completed human trials.

    KPV is a three-amino-acid fragment of alpha-MSH, and its mechanism is unusually well-characterized for a compound this size. It enters intestinal and immune cells through the PepT1 transporter, the same carrier that handles dipeptides and tripeptides from digested dietary protein, and once inside, it interferes with the importin-alpha3/p65RelA complex, blocking NF-kB nuclear translocation and suppressing downstream inflammatory cytokines (TNF-alpha, IL-1, IL-6).

    The animal data is genuinely strong: DSS and TNBS mouse colitis models (Dalmasso 2008, Kannengiesser 2008) show meaningful reductions in inflammatory markers. The problem is the translation step. DSS/TNBS mouse colitis models have historically translated to human outcomes at only 10-15%, a sobering number for any compound whose entire efficacy case currently rests on mouse data. Zero completed human RCTs exist for KPV in any indication.

    MOTS-c

    Grade: D. The clearest correlation-vs-causation trap of the six.

    MOTS-c is a 16-amino-acid peptide encoded directly in mitochondrial DNA, discovered in 2015. The animal data (primarily mice) shows real effects on insulin sensitivity, inflammatory markers, and glucose homeostasis.

    The human data that exists is purely observational: exercise increases circulating MOTS-c levels in skeletal muscle and blood. That’s a real finding, but it’s a correlation between exercise and a biomarker, not a controlled trial testing whether giving someone exogenous MOTS-c produces a treatment effect. No published human interventional trial has tested that question. The gap between “your body makes more of this when you exercise” and “taking more of this replicates exercise’s benefits” is exactly the kind of gap that’s easy to paper over with hopeful language, and worth naming directly instead.

    Epitalon

    Grade: D. Same literature-access problem as Semax.

    Epitalon carries a near-legendary reputation in longevity circles, and its research history runs into the same issue as Semax: a real body of work exists, much of it Russian in origin, and much of it sits outside what’s easily searchable in English-language databases. The same caveat applies here as it did for Semax: this is a documented pattern worth naming, not a fully verified claim that resolves the evidence gap.

    The pattern across all six

    Every one of these compounds has a plausible, often well-characterized mechanism. Every one has real preclinical (mostly animal) data supporting that mechanism. And every one is missing the thing that actually determines whether a compound works in people: a completed human clinical trial.

    That’s not a condemnation of any of them. Plenty of compounds with this exact profile eventually clear that bar. It’s just the honest state of the evidence right now, and it’s worth being precise about it independent of the regulatory news cycle.

    Here’s the distinction that matters most going forward: a 503A compounding recommendation, if the FDA eventually adopts it, changes the legal pathway for these compounds. It does not change the evidence. Those are two separate axes, and it’s worth not letting a genuinely significant regulatory story get mistaken for a medical one.

    We’ll keep grading these as the literature moves. If any of the six clears a real human trial, that’s the post that follows this one.

  • The Retatrutide Court Case: What’s Actually at Stake

    Troy Snyder, Sept 2026

    If you’ve been tracking Retatrutide’s evidence record with us — the TRIUMPH trials, the June Lancet publication, the EASD data landing September 30 — there’s a separate story developing this week that has nothing to do with clinical data and everything to do with whether any of it matters in the way you’d expect.

    On September 21, the DOJ filed a letter in Eli Lilly v. FDA (7th Circuit, No. 26-1301), a case that’s been quietly working through the courts and is about to get a lot louder. Oral arguments are Thursday, September 24, 9:30am, Chicago.

    What the case is actually about

    Strip away the legal language and it comes down to one question: is Retatrutide a peptide drug, or is it a protein/biologic?

    That sounds like a technicality. It isn’t. The two classifications sit inside completely different regulatory frameworks, and which one Reta lands in determines the entire competitive landscape around it going forward.

    • Lilly’s position: Retatrutide should be classified as a protein/biologic.
    • FDA’s position: It’s a peptide drug and doesn’t meet the agency’s own definition of a protein.

    The DOJ’s letter this week is procedural but consequential — it’s pointing the appeals court toward a recent Seventh Circuit precedent (Franco v. Chobani, 2026) holding that when an agency’s interpretation of its own scientific definitions is at issue, that interpretation can still carry significant weight with courts, even post-Chevron. In plain terms: DOJ is telling the judges not to second-guess FDA’s classification lightly.

    Why the classification actually matters

    If Reta gets classified as a biologic:

    • Follow-on/generic-equivalent products go through the biosimilar pathway instead of the standard generic route — a slower, more expensive approval process historically reserved for large, complex molecules.
    • 503A/503B compounding pharmacies lose their normal drug-compounding exemptions for biologics, which changes who can legally produce Reta-adjacent formulations and under what rules.

    If Reta stays classified as a peptide drug:

    • It remains inside the traditional drug framework, where standard generic pathways apply.
    • 503A/503B compounding exemptions can still apply, provided other regulatory requirements are met.

    Neither outcome is good or bad in the abstract but they’re genuinely different worlds for anyone tracking availability, pricing, and the broader compounding/RUO ecosystem that sits adjacent to this compound’s supply chain.

    What this means for the grey market

    The 503A/503B compounding question isn’t just a pharmacy-industry detail, it’s the actual bridge between this court case and the broader research-peptide ecosystem, RUO sourcing included.

    If Reta moves into the biosimilar framework, compounding pharmacies lose the exemptions that currently let them produce Reta-adjacent formulations more freely. That tends to push demand in one of two directions, and it’s genuinely unclear which wins out:

    • Tighter compounding rules could push more demand toward RUO/research-only channels as the compounding pathway narrows, the same pattern seen with other GLP-1 compounds when compounding pharmacies faced restrictions.
    • Or it could do the opposite: a high-profile classification fight tends to put the entire peptide category under a brighter regulatory spotlight, RUO sourcing included, not just the specific compound in litigation. Increased scrutiny on one part of the ecosystem has historically spilled over into stricter enforcement, platform bans, and payment-processor caution across the board — something we’ve experienced directly this month.

    We’re not going to speculate on which direction wins, because neither outcome is something we’d base a customer-facing claim on before it actually happens. What we can say plainly: this case is worth watching regardless of whether you buy compounded, RUO, or anything else in this space. The ruling reshapes incentives for the whole supply chain, not just Lilly’s own product line.

    What we’re watching for

    We’ll be straight about where we sit on this: we don’t have a legal opinion on how the classification question should be decided, that’s genuinely a matter for the courts to work out, and we’re not lawyers. But we do have a rooting interest, and we’re not going to pretend otherwise. If Reta stays classified as a peptide drug, the compounding and RUO ecosystem this whole site operates in keeps more room to breathe. If Lilly wins, that room narrows. That’s not a legal argument for either side, it’s just an honest disclosure of where our interest lies, same as we disclose our ownership stake in Agape on multiple pages of this site.

    Oral arguments are Thursday. A ruling likely won’t land immediately; appellate decisions in cases like this often take weeks to months after arguments, but the reasoning that comes out of Thursday’s session will be the first real signal of which way this is heading.

    We’ll cover the outcome in Grade Changes once there’s something concrete to report. For now, this is a “know it’s coming” post, not a “here’s the answer” post — and we’d rather tell you that plainly than manufacture certainty we don’t have.

    — Troy

    Peptide Briefs is an independent research library. This piece covers regulatory proceedings, not clinical evidence — Retatrutide’s evidence grade (B) is unaffected by this case and is tracked separately.

  • What a 60%-Off Sale Actually Tells You About a Peptide Supplier

    Troy Snyder, September 2026

    If you’ve spent any time in peptide research circles this month, you’ve seen it: sitewide discounts stacking past 50%, automatic markdowns on top of promo codes, giveaways for anyone who checks out with the right code. One vendor pairs a 45% automatic discount with another 15% off code and calls it “no end date.” Another runs Buy-One-Get-One on top of a percentage code that, stacked correctly, works out to over 60% off per vial.

    It’s tempting to read that as a good deal. It’s worth reading it as a question instead: how does a business built around third-party testing, verified sourcing, and cold-chain shipping sustain a discount that deep, indefinitely, and still stay in business?

    There are really only three ways the math works.

    One: the margin was never that thin to begin with. If a sitewide “sale” price still covers costs at 60% off, the pre-sale price wasn’t reflecting real costs — it was reflecting what the market would bear before the next promo. That’s not illegal. It’s just worth knowing that “sale price” and “fair price” aren’t the same claim.

    Two: something in the process is getting cut to make the discount work. Third-party testing costs money per batch ($200 to $500 per vial depending on the peptide and tests). Verified cold-chain shipping costs money per order. A cryptographically signed Certificate of Analysis, one you can actually verify yourself, not just a PDF with a lab’s letterhead on it costs more than a basic identity check. When the discount is deep enough and permanent enough, ask which of those got quietly thinned out to protect the margin.

    Three: it’s a customer-acquisition strategy, not a pricing strategy. Giveaways, referral drawings, “round two” prize drawings for anyone who already bought these are list-building and retention plays. Nothing wrong with that on its own. But it means the price you’re looking at was never really about the product. It was about winning your business away from whoever you were buying from before, permanently discounted forever, funded by volume rather than margin.

    None of this means every vendor running a deep discount is cutting corners. Some genuinely have better supplier costs and are passing it through, which we are always trying to find and pass on to our customers. That’s the honest version of price competition, and it’s real. The problem is you can’t tell the difference from the discount percentage alone. A 60% off badge tells you nothing about purity. It tells you the marketing team is good at their job.

    So what should you actually check, instead of chasing the number?

    • Is the COA batch-specific, or generic? A Certificate of Analysis tied to the exact lot number on your product is worth infinitely more than a “representative” COA posted once and reused across restocks.
    • Can you verify the signature independently? A cryptographically signed COA (verifiable through the testing lab’s own portal, not just trust-the-PDF) means the document can’t be quietly edited after the fact. Most suppliers don’t offer this because most testing labs don’t offer it standard. It costs more.
    • What method did the testing actually use? UV-Vis identity testing is common and it’s honest as far as it goes, but it can’t distinguish some closely related compounds from each other. HPLC and LC-MS can. If a vendor doesn’t say which method was used, that’s the question to ask before you ask about price.
    • Does the discount depend on you never checking again? The vendors worth trusting are the ones who’d still pass this test at full price. If the pitch only works because you’re excited about the percentage, the pitch is doing the work the product should be doing.

    We built Peptide Briefs on the opposite bet: that researchers would rather know exactly where the evidence stands, including the compounds we grade a C, including the batches that failed identity testing and got discarded rather than shipped, than be sold on a discount that changes weekly. That’s also why every Agape Compounds batch carries a signed, independently verifiable COA rather than a static PDF. We’d rather be the supplier you checked and trusted than the one you almost forgot to check because the price looked good.

    The next time a sitewide discount crosses 50%, don’t ask “how do I stack this.” Ask what it would honestly cost to run this business, then ask why this price doesn’t reflect that.

    — Troy

    Peptide Briefs is an independent research library. We test, grade, and document. We don’t chase the discount war.

  • 5 Red Flags That Separate a Legitimate Peptide Supplier from a Sketchy One

    5 Red Flags That Separate a Legitimate Peptide Supplier from a Sketchy One

    If you have spent any time shopping for research peptides, you already know the feeling: the packaging looks sharp, the website is polished, the prices are either suspiciously low or suspiciously high, and underneath all of it sits one unanswerable question.

    Is this supplier actually legitimate?

    It is a fair question to ask, and an uncomfortable one to ask out loud. Most buyers in this category are not looking for a bargain. They are looking for consistency: the same compound, the same purity, the same documentation, order after order. The trouble is that the signals which separate a careful supplier from a careless one are rarely advertised. You have to know where to look.

    Below are five red flags worth checking before you place an order, and what good practice looks like when a supplier is doing it right. None of this is about a single company. It is a checklist you can apply anywhere, including to us.

    Red flag 1: No certificate of analysis, or one you have to beg for

    A certificate of analysis (COA) is the single most useful document in this market. It records what was actually tested in a given batch: identity, purity, and the analytical method used to establish them, usually high-performance liquid chromatography (HPLC) or mass spectrometry (MS).

    The red flag is not a missing PDF on the homepage. It is a COA that only appears after three emails, that arrives with the batch number blanked out, or that lists purity to two decimal places with no method, no laboratory name, and no date.

    What good practice looks like: the COA is available before purchase, it matches the batch number printed on the vial you receive, and it names the testing method and the date of analysis. If a supplier cannot tell you which batch a document belongs to, the document tells you very little.

    Red flag 2: Purity claims with no method behind them

    “99% pure” is a marketing sentence until someone tells you 99% of what, measured how.

    Peptide purity is a real, measurable quantity, but it is also easy to state loosely. A supplier who advertises a purity figure without naming the analytical method, the testing laboratory, or the batch is asking you to take the number on faith. That is the opposite of how analytical chemistry works.

    What good practice looks like: purity figures are tied to a specific batch, a specific method, and a specific date. Where a supplier publishes third-party testing, even better. Documentation is not a marketing asset. It is a record, and records have dates.

    Red flag 3: Pressure pricing and manufactured urgency

    Countdown timers. “Only 4 left” on a compound that is synthesized to order. A discount that expires in twenty minutes and reappears tomorrow.

    Urgency is a retail technique, not a laboratory one. In a category where the product is a measured chemical and the buyers are frequently researchers, manufactured scarcity is a tell. It suggests the seller is optimizing for a fast transaction rather than a repeat relationship, and repeat relationships are the only kind that matter in this market.

    There is a second, subtler version of this flag: prices that swing wildly between visits. Real supply costs move slowly. If a listing price is different every week with no explanation, the seller may be testing what the traffic will bear rather than pricing a product.

    What good practice looks like: stable, plainly stated pricing, transparent shipping terms, and no theatrics.

    Red flag 4: No real contact information

    A supplier who cannot be reached before a sale is unlikely to be reachable after one.

    Check for a physical business address, a working phone line or a monitored email address, and terms that name the legal entity behind the storefront. A contact form that routes into a void, a support email that bounces, or terms of service copied verbatim from an unrelated site are all signs that the operation is thin.

    What good practice looks like: verifiable contact details, a named entity, clear terms, and a human response within a reasonable window. Support quality before purchase is the best available preview of support quality after.

    Red flag 5: Inconsistency between batches

    This is the most important flag, and the hardest to spot from the outside.

    A compound that arrives as a fine white powder one month and a clumped, discolored mass the next is not necessarily contaminated, but it does mean something changed. Batch-to-batch consistency is the entire point of buying from a serious supplier instead of a marketplace listing. When the product, the documentation, or the packaging shifts without explanation, the supplier is telling you how much process control sits behind the label.

    What good practice looks like: batch numbers that change while everything else stays constant, matching documentation for each batch, and honest disclosure when a batch is reformulated, restocked, or delayed.

    What to do with this list

    Run the five checks in order. Ask for the COA before you buy and confirm the batch number matches the vial you receive. Ask which method established the purity figure. Ignore the timer. Send a question to support and see who answers and how quickly. Compare your last three orders from the same supplier and look for drift.

    Then ask the same questions of whoever you buy from next, including us. A supplier who is confident in their process will not mind the questions. That confidence is the product, and it is the only one worth paying for.

    One note on scope, since it matters for reading everything above correctly: research peptides are sold for laboratory and research use, not for human consumption, and no part of this article is medical advice or a claim about any compound’s effects in people. What we are describing here is procurement hygiene: how to tell whether the vial in your hand matches the paperwork that came with it.

    At Agape Compounds, every order ships with a full certificate of analysis, purity figures tied to the batch you receive, discreet and secure shipping, and a support team that answers questions before a sale rather than after. Rooted in faith, driven by science. Vet us like you would vet anyone else.